








MATCH is the second stage of the Care Map Method™. Once the need is mapped, the work turns to the right person, provider, setting, support or program. The standard is the map itself. Options are compared against the needs and constraints already named, rather than against charm, availability or a general idea of quality.
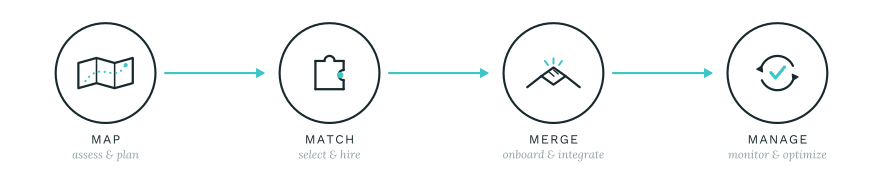
Within MAP → MATCH → MERGE → MANAGE™, this stage converts understanding into a choice. It does not ask whether an option is good in the abstract. It asks whether that option fits this person, this household or this organization, under the conditions that actually exist.
What MATCH Actually Is
MATCH is a structured comparison between the map and the available options. The map supplies the criteria: the role to be filled, the needs to be met, the boundaries that matter and the conditions that cannot be changed. The matching process then looks for alignment across those criteria.
Fit is broader than competence. A caregiver can have strong experience and still be wrong for a household's schedule or communication style. A care setting can offer appropriate support and still work against a person's identity or relationships. A product can function well and still ask a family to carry more coordination than it can manage.
Matching keeps the whole person visible. Biological, Social, Environmental and Emotional² needs remain connected, so one strong feature does not erase a serious mismatch elsewhere.
What Goes Wrong When MATCH Is Skipped
When MATCH is skipped, selection is driven by what is easiest to see. Families may choose warmth in an interview, a polished tour or the first opening on a difficult week. Organizations may choose a familiar category, a broad feature list or a compelling demonstration without testing the fit against the people the program is meant to serve.
The mismatch often appears later as a management problem. Expectations are repeated, boundaries tighten and the people involved work harder. Yet effort cannot repair a choice that never matched the mapped need. The arrangement keeps asking everyone to compensate for a gap built into the selection.
A rushed match can also confuse urgency with permission to lower the standard. The map helps identify which criteria are essential and which can flex, allowing a timely decision without abandoning the person at the center of it.
What MATCH Looks Like for a Family
For a family, MATCH begins before the interview, tour or consultation. The family turns the map into questions and observable criteria. It names the practical requirements, the relationship dynamics, the communication style and the emotional needs that the arrangement must respect.
Candidates and settings can then be considered through real situations instead of broad promises. The family can ask how an option would handle a changing schedule, a difficult transition, a disagreement about roles or a need for autonomy. The goal is not certainty. It is a choice grounded in the family's own definition of fit.
What MATCH Looks Like for an Organization
For an employer, health tech team or care platform, MATCH can shape referral logic, provider criteria, benefit selection and content pathways. It asks whether the route from need to option reflects the full care situation or reduces a person to one presenting problem.
A stronger matching structure makes the criteria visible. Teams can explain why an option is being presented, what it addresses and what remains outside its scope. That clarity supports responsible product and program design while preserving the role of human judgment where the map requires it.
MATCH turns the map into a disciplined choice. The next stage is MERGE, where that choice has to enter real life through explicit roles, routines and expectations.
Care Map consulting and advisory work is educational and strategic. It is not diagnosis or treatment and does not create a therapist–client relationship.